
 PV
 TG
 MN
 EM
 EI
 ND

 CT Scan
 PET CT
 Digital X-ray
 Ultrasound
 Amniocentesis

 Fetal Reduction
 Thermalytix Breast Screening
 Cardiology
 Lab Tests
 GAMCA Pre-Medical
Amnioinfusion is a procedure in which warmed, sterile fluid — usually normal saline or Ringer’s lactate — is placed into the amniotic sac around the baby. Before labour it is done through a fine needle passed through the mother’s abdomen under continuous ultrasound guidance, a technique called transabdominal amnioinfusion.
If your doctor has mentioned amnioinfusion, it is almost always because a scan has shown too little amniotic fluid (oligohydramnios), or because the waters have broken early. Those are worrying words to hear in pregnancy, and the internet is full of confusing claims about procedures that “increase amniotic fluid”. This guide explains, in plain language, what amnioinfusion actually is, the two very different situations in which it is used, what it can and cannot achieve, how the amnioinfusion procedure is done step by step, the honest risks, and what the results mean.
It is general information, not a decision. That belongs to you and your obstetrician or fetal medicine specialist.
Amnioinfusion at a glance
- What it is: putting warmed sterile fluid into the amniotic sac to replace fluid that is missing
- Two types: transabdominal (through the abdomen with a needle, before labour, under ultrasound) and transcervical (through a thin catheter in the cervix, during labour, in the labour room)
- Main uses before labour: to let the baby be seen clearly on ultrasound when fluid is very low, to help confirm whether the waters have broken, and in selected cases of early severe low fluid
- Main use in labour: to cushion the umbilical cord when the baby’s heart-rate pattern suggests the cord is being squeezed
- How long: the transabdominal procedure itself usually takes about 20 to 45 minutes
- Anaesthesia: local anaesthetic in the skin; no general anaesthesia
- Main limitation: it replaces fluid but does not fix the reason the fluid was low, so the fluid is often lost again
- Main risks: leaking of fluid, infection, preterm labour and, rarely, pregnancy loss — broadly similar to amniocentesis, and higher if the membranes have already ruptured
What this guide covers
- What amnioinfusion is
- Transabdominal vs transcervical amnioinfusion
- Why amniotic fluid matters
- Why amnioinfusion is done: the main uses
- Amnioinfusion to see the baby clearly
- Amnioinfusion to check whether the waters have broken
- Amnioinfusion after early rupture of membranes (PPROM)
- Amnioinfusion for oligohydramnios: what it can and cannot do
- Amnioinfusion during labour
- Amnioinfusion and meconium: what changed
- When amnioinfusion is not done
- Before the procedure
- How the amnioinfusion procedure is done, step by step
- What fluid is used and how much
- Does amnioinfusion hurt?
- Amnioinfusion risks: the honest picture
- After the procedure
- Results: what it can show and how long the fluid lasts
- Amnioinfusion vs amnioreduction vs amniocentesis
- Other ways low amniotic fluid is managed
- Questions to ask your doctor
- What to expect on the day
- Prenatal procedures and the law
- Amnioinfusion in Delhi: where it is done
- References
- Frequently asked questions
What amnioinfusion is
Throughout pregnancy the baby floats in amniotic fluid inside a thin, two-layered sac called the membranes. Amnioinfusion simply means infusing fluid into that sac. The fluid used is not a medicine; it is a sterile salt solution very similar in make-up to body fluids, warmed to body temperature so that it does not chill the baby or irritate the womb.
The idea is straightforward. If there is too little fluid around the baby, putting some back can do three useful things. It can create a clear “window” through which ultrasound can see the baby’s organs. It can show whether fluid is leaking out of the vagina, which helps confirm that the waters have broken. And during labour, it can float the umbilical cord away from being squeezed between the baby and the wall of the womb.
What amnioinfusion cannot do is permanently correct the cause of low fluid. Amniotic fluid in the second half of pregnancy is mostly the baby’s urine. If the fluid is low because the baby’s kidneys are not making urine, or because the membranes have a tear through which fluid keeps leaking, or because the placenta is not working well, then the fluid that is put in will usually leak away or be absorbed over the following hours to days. Understanding this one point avoids a great deal of disappointment, and it is why responsible specialists describe amnioinfusion as a tool for specific purposes rather than a cure for low fluid.
You may also see amnioinfusion described as “a procedure to increase amniotic fluid” or even “surgery to increase amniotic fluid”. There is no open surgery involved. The transabdominal amnioinfusion procedure is a needle procedure performed under ultrasound, much like an amniocentesis, and the “increase” it produces is usually temporary.
Transabdominal vs transcervical amnioinfusion
The single most important thing to understand about amnioinfusion is that the word covers two procedures done in completely different settings, for different reasons.
| Transabdominal amnioinfusion | Transcervical amnioinfusion | |
|---|---|---|
| When | Before labour, usually in the second or early third trimester | During labour, after the waters have broken |
| Route | Fine needle through the abdomen and the wall of the womb | Thin soft catheter passed through the open cervix |
| Guidance | Continuous ultrasound | Placed by touch during a vaginal examination; ultrasound not needed for placement |
| Where it is done | A fetal medicine or imaging unit with procedure facilities | The hospital labour room, by the obstetric team |
| Main purposes | Better ultrasound views, confirming rupture of membranes, selected cases of early severe low fluid | Relieving umbilical cord compression shown on fetal heart monitoring |
| Who performs it | Fetal medicine specialist or experienced interventional radiologist / sonologist | The obstetrician managing the labour |
At a diagnostic and imaging centre like ours, the procedure that is relevant is transabdominal amnioinfusion, done before labour, on an obstetrician’s referral. Amnioinfusion during labour is an obstetric decision made at the bedside in the hospital where you are delivering, and it is described here only so that you understand the difference.
Why amniotic fluid matters
Amniotic fluid is not just padding. It lets the baby move and stretch, which helps the muscles and joints develop. It is breathed in and out by the baby, which is essential for the lungs to grow, especially between about 16 and 24 weeks. It cushions the umbilical cord so that the blood supply to the baby is not interrupted when the womb tightens. And it helps protect against infection.
On ultrasound, fluid is measured in one of two ways. The deepest vertical pocket (DVP) is the depth of the single largest clear pocket of fluid. The amniotic fluid index (AFI) adds together the deepest pocket from each of the four quarters of the womb. Fluid is usually described as low — oligohydramnios — when the DVP is under 2 cm or the AFI is 5 cm or less. When there is essentially no measurable fluid at all, the term anhydramnios is used.
Low fluid has many causes, and they matter far more than the number itself. The commonest are early rupture of the membranes, a placenta that is not supplying the baby well (often with poor growth), a pregnancy that has gone past its due date, problems with the baby’s kidneys or urinary tract, and certain medicines such as some painkillers and blood-pressure tablets. Sometimes, particularly late in pregnancy, no cause is found and the outlook is good. Our full guide to low amniotic fluid (oligohydramnios) covers the causes, risks and what genuinely helps.
The stage of pregnancy matters too. Low fluid near term is common and is usually managed by monitoring and planning delivery. Severe low fluid in the second trimester, before about 24 weeks, is a more serious situation, because the baby’s lungs need fluid to grow and a long period without it can lead to underdeveloped lungs (pulmonary hypoplasia) and stiff joints. It is in this earlier, more serious group that transabdominal amnioinfusion is most often discussed.
Why amnioinfusion is done: the main uses
Amnioinfusion is never done simply because a fluid number is low. It is done when putting fluid back will answer a question or solve a specific problem. The main reasons are summarised below and then explained one by one.
| Purpose | Type | What it aims to achieve | How strong is the evidence? |
|---|---|---|---|
| Diagnostic: better ultrasound views | Transabdominal | Creates an acoustic window so the baby’s kidneys, bladder, heart, spine and limbs can be assessed properly | Well established as a diagnostic aid in experienced hands |
| Confirming rupture of membranes | Transabdominal | Shows whether instilled fluid appears in the vagina when ordinary tests are inconclusive | Used occasionally; most cases are confirmed without any needle |
| Early severe low fluid or early PPROM | Transabdominal, sometimes repeated | Tries to give the baby’s lungs and limbs room and fluid to develop | Limited and mixed; should be discussed as uncertain |
| Creating space for another fetal procedure | Transabdominal | Gives room to place a shunt or perform a procedure safely | Specialist fetal medicine use only |
| Cord compression in labour | Transcervical | Cushions the cord to improve the baby’s heart-rate pattern | Supported by trials, though most were small; one option among several |
| Routine use for meconium in labour | Transcervical | Was thought to dilute meconium | Not recommended — a large trial showed no benefit |
Amnioinfusion to see the baby clearly
Ultrasound images are formed by sound waves, and sound travels beautifully through fluid. When there is plenty of amniotic fluid, the baby is surrounded by a dark, clear space and every organ stands out. When the fluid is very low, the baby is pressed against the wall of the womb and the placenta, the sound has nothing to travel through, and the pictures become grey and blurred. Important structures can be impossible to see.
This matters most when the low fluid itself might be caused by a problem with the baby. The classic example is the kidneys. If both kidneys are absent or not working, the baby makes no urine and there will be almost no fluid — but the very lack of fluid makes it hard to confirm whether the kidneys are there. A diagnostic transabdominal amnioinfusion creates a fluid window so that the kidneys, the bladder and the blood vessels to the kidneys (with colour Doppler) can be examined properly. The heart, spine, face and limbs can also be checked much more reliably.
The result can change management completely. If the baby’s anatomy looks normal and the fluid quickly leaks out through the vagina, the problem is most likely ruptured membranes. If the kidneys and bladder can be seen and look normal, a kidney cause becomes less likely. If a serious structural problem is found, parents can be counselled with much greater certainty than a blurred scan allows.
Because a needle is already in place, a small sample of amniotic fluid can sometimes be taken at the start of the procedure for genetic testing, if that has been discussed and agreed beforehand. In very low fluid there may not be enough to sample until some fluid has been infused, and the specialist will explain how this is handled. Any such testing looks only for genetic and chromosomal conditions.
Amnioinfusion to check whether the waters have broken
Most of the time, whether the waters have broken is decided without any needle at all: a speculum examination to look for fluid pooling, simple bedside tests on the fluid, and an ultrasound of the fluid volume. These are enough in the great majority of women.
Occasionally the picture remains unclear — for example, there is a history of a gush of fluid, the tests are equivocal and the scan shows low fluid, but the answer would genuinely change what happens next. In that situation a specialist may consider instilling fluid into the sac, sometimes with a harmless dye, and then checking whether it appears on a pad or tampon placed in the vagina. If it does, the membranes have ruptured. Methylene blue dye is not used, because it is known to be harmful to the baby. This use of amnioinfusion is uncommon today and is a decision for the specialist team.
Amnioinfusion after early rupture of membranes (PPROM)
Preterm prelabour rupture of membranes (PPROM) means the waters break before 37 weeks and before labour starts. When it happens very early — in the second trimester — fluid can stay very low for weeks, and the baby’s lungs may not develop properly.
It is natural to think that topping the fluid back up must help. Researchers have tested exactly this, using transabdominal amnioinfusion once or repeatedly in women with PPROM before about 26 weeks. The results so far have been disappointing and uncertain. A Cochrane systematic review of transabdominal amnioinfusion after early PPROM found the trial evidence too limited to recommend it as routine treatment, and called for more and larger studies. Other trials have not shown a clear improvement in survival or in the time gained before delivery.
The practical reason is simple: if the membranes have a tear, the infused fluid leaks out, often within hours to a few days. Repeated procedures add their own risks of infection and labour. For these reasons, amnioinfusion after early PPROM is generally offered, if at all, after careful counselling in a specialist fetal medicine setting, or as part of research. The standard care of PPROM — antibiotics, steroids to mature the baby’s lungs when appropriate, close monitoring for infection, and planning the timing of delivery — remains the backbone of management and is decided by your obstetrician.
Amnioinfusion for oligohydramnios: what it can and cannot do
Many families search for amnioinfusion for oligohydramnios hoping for a procedure that will fix low fluid. It is important to be honest about what it offers.
What amnioinfusion for oligohydramnios can do:
- Allow a detailed, reliable scan of the baby when low fluid makes the scan unclear
- Help work out why the fluid is low — leaking membranes, a kidney or bladder problem, or something else
- Allow a fluid sample for genetic testing at the same sitting, where this has been agreed
- In carefully selected cases, be tried as a therapeutic measure under specialist supervision, with the uncertainty explained
What it cannot do:
- Repair torn membranes
- Make absent or non-working kidneys produce urine
- Improve a placenta that is not working well
- Keep the fluid at a normal level permanently in most cases
- Replace close monitoring and good timing of delivery, which remain the most important tools for low fluid later in pregnancy
For example, in a baby with a blockage of the lower urinary tract, the bladder becomes swollen and fluid is low. Serial amnioinfusion has been tried in such cases, but an international expert consensus has advised that it should be offered only within research settings. Where a procedure is considered in this situation, it is usually a different one — such as placing a shunt to drain the bladder — in a specialist fetal medicine centre.
Low fluid near the due date is a different situation again. There, amnioinfusion is not used to raise the fluid before labour. The usual approach is monitoring the baby’s wellbeing and, where appropriate, planning delivery.
Amnioinfusion during labour
During labour, the womb contracts strongly every few minutes. If there is little fluid around the baby, the umbilical cord can be squeezed with each contraction. On the fetal heart monitor this shows up as repeated, sharp dips in the baby’s heart rate called variable decelerations.
Transcervical amnioinfusion is one of the ways obstetricians respond to this. Once the waters have broken and the cervix has opened, a thin soft tube (often an intrauterine pressure catheter) is passed into the womb beside the baby’s head, and warmed saline is run in slowly. The extra fluid can cushion the cord and the heart-rate pattern often improves. A Cochrane review of amnioinfusion for suspected cord compression in labour found that it appears to reduce the occurrence of heart-rate decelerations and the need for caesarean section for fetal distress, though the reviewers noted the trials were small and not all of high quality.
Where it is used, amnioinfusion is always one option among several — changing the mother’s position, giving fluids, stopping contraction-strengthening drugs and, if needed, expediting delivery. This is entirely a labour-room decision, made at the bedside by the obstetrician in the hospital where you deliver.
Amnioinfusion and meconium: what changed
Meconium is the baby’s first stool. If it is passed into the amniotic fluid before birth, the fluid becomes stained green or brown, and occasionally the baby breathes it into the lungs, causing meconium aspiration syndrome.
For some years, amnioinfusion was used during labour to dilute thick meconium, in the hope of preventing this. A large international randomised trial published in 2005, involving close to two thousand women with thick meconium, found that amnioinfusion did not reduce meconium aspiration syndrome or perinatal death. Since then, routine amnioinfusion simply to dilute meconium has not been recommended. If you read older information suggesting otherwise, it is out of date. Amnioinfusion may still be used in labour for a different reason — cord compression — when the obstetrician judges it appropriate.
When amnioinfusion is not done
Like any invasive procedure, amnioinfusion is not right for everyone. Your specialist will usually advise against it, or choose another approach, when:
- There are signs of infection inside the womb (chorioamnionitis), such as fever, a raised pulse, tenderness of the womb or offensive discharge
- There is significant vaginal bleeding or a suspected placental abruption
- Labour is established and delivery, rather than a procedure, is the safer course
- The baby shows signs of serious distress that need urgent delivery
- The result would not change management, so the risks are not justified
- There is no safe route for the needle, for example because of the placenta’s position combined with very little fluid
- The mother has an infection that could be passed to the baby by a needle procedure, unless the specialist judges the benefit clearly outweighs this
None of these is a reason to panic. They are simply the questions a careful specialist works through before recommending any needle procedure in pregnancy.
Before the procedure
A transabdominal amnioinfusion is planned, not rushed. Before the day, you can expect the following.
- A referral and a discussion. Your obstetrician or fetal medicine specialist explains why it is being suggested, what question it should answer, and what will happen depending on the result.
- A review of your scans. Recent ultrasound reports, fluid measurements, growth measurements and Doppler findings are reviewed. A fresh scan is usually done on the day as well.
- Blood group. If your blood group is Rh negative, you will usually need an anti-D injection after the procedure, as with any needle procedure in pregnancy.
- Infection screening. Results for HIV, hepatitis B and hepatitis C are checked where available, because they influence the decision and the precautions taken.
- Medicines. Tell the team about any blood thinners, aspirin or other regular medicines. Do not stop anything without your doctor’s advice.
- Consent. You will be asked to sign a consent form after the purpose, the alternatives, the risks and the likelihood of fluid being lost again have been explained. You are free to ask questions or to decline.
There is usually no need to fast. Eat a light meal, drink normally unless told otherwise, and bring a companion so that you do not have to travel home alone.
How the amnioinfusion procedure is done, step by step
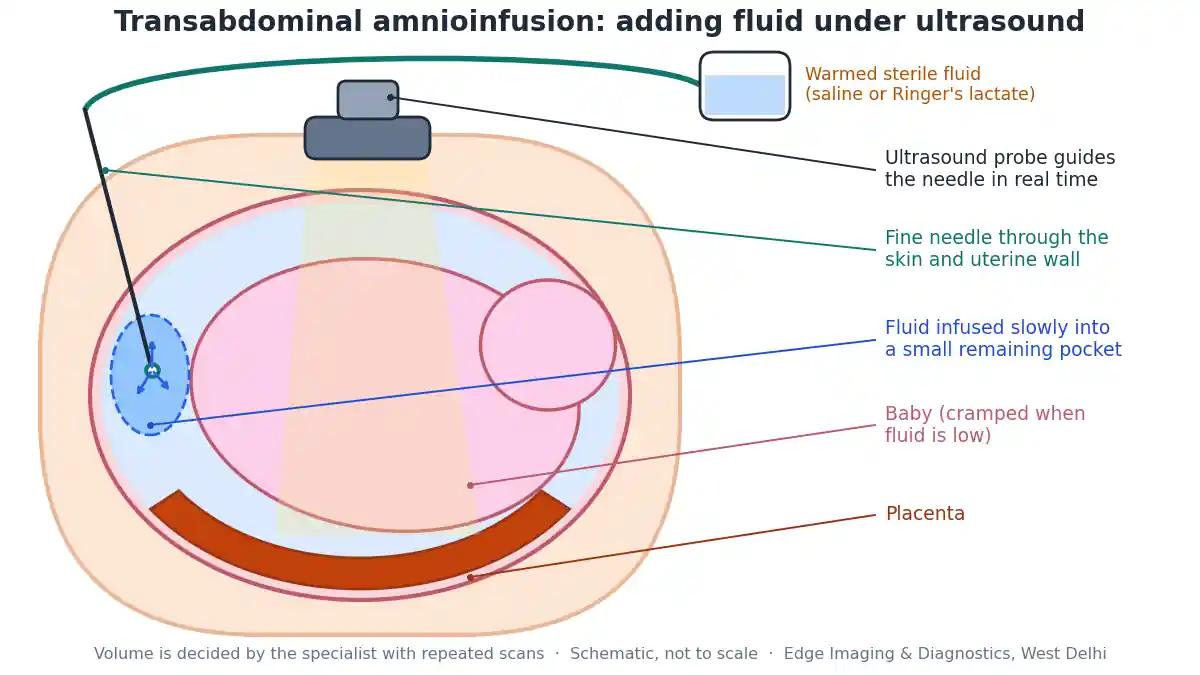
The transabdominal amnioinfusion procedure follows a careful, unhurried sequence.
- Scan first. An ultrasound confirms the baby’s heartbeat and position, where the placenta lies, the amount of fluid, and the safest point of entry. With very low fluid, finding a small pocket away from the baby’s face, the cord and the placenta takes skill and patience.
- Clean and numb. The skin of the abdomen is cleaned with antiseptic and covered with sterile drapes. Local anaesthetic is injected into the skin at the entry point.
- Needle placement. A fine needle is passed through the skin and the wall of the womb into the chosen pocket, with the needle tip watched on the ultrasound screen the whole time.
- Confirming position. A tiny amount of fluid is drawn back, or a small test volume is injected and seen spreading on the screen, to confirm the tip is in the amniotic sac.
- Sample, if planned. If a genetic test has been agreed, a sample is taken at this point.
- Slow infusion. Warmed sterile saline or Ringer’s lactate is infused slowly, by syringe or through a drip set. The fluid can be seen opening up a dark, clear space around the baby.
- Repeated checks. The baby’s heart rate is checked during the procedure, and the amount of fluid is re-measured as the infusion progresses.
- Detailed scan. Once a useful window has been created, the specialist performs the detailed assessment of the baby’s anatomy — often the main purpose of the whole procedure.
- Needle removal. The needle is withdrawn and a small dressing applied. A final check of the baby’s heartbeat is made.
The whole visit usually takes one to two hours including preparation and observation, though the needle itself is in place for a shorter time.
What fluid is used and how much
The fluid is a sterile, physiological solution — normal saline or Ringer’s lactate — warmed to body temperature. Warming matters: cold fluid can cause the womb to contract and can upset the baby’s heart rate. No medicine or hormone is added. If a dye is used to check for leaking membranes, it is one considered safe in pregnancy.
The volume is not fixed. It depends on the stage of pregnancy, how much fluid is already present, the purpose of the procedure and how the baby and the womb respond. Commonly a few hundred millilitres are infused, enough to bring the deepest pocket back towards the normal range and give a good view. Overfilling is avoided, because too much fluid can make the womb tense and trigger contractions.
Does amnioinfusion hurt?
Most women describe it as uncomfortable rather than painful. The local anaesthetic stings for a few seconds. When the needle passes through the wall of the womb there may be a brief sharp or pressing sensation. During the infusion, some women feel a sense of fullness or mild period-like cramping. General anaesthesia is not used, and you remain awake and able to talk to the team throughout. Tell the team at once if the pain becomes strong; they can pause.
Amnioinfusion risks: the honest picture
Amnioinfusion risks are broadly similar to those of amniocentesis, but they need to be understood in context. The procedure takes longer than a routine amniocentesis, and it is usually done in a pregnancy that is already complicated by very low fluid or ruptured membranes, which carries risks of its own. Your specialist will give you figures that apply to your own situation.
| Risk | What it means | How it is reduced |
|---|---|---|
| Leaking of fluid / rupture of membranes | Fluid may leak through the vagina afterwards, especially if the membranes were intact before | Fine needle, single entry where possible, slow infusion |
| Infection (chorioamnionitis) | Infection inside the womb, which can be serious for mother and baby | Strict sterile technique; not performed if infection is already suspected |
| Preterm contractions or labour | The womb may tighten or labour may start | Warmed fluid, avoiding overfilling, observation afterwards |
| Bleeding or placental abruption | Rare bleeding at the needle site or separation of the placenta | Avoiding the placenta where possible; continuous ultrasound guidance |
| Changes in the baby’s heart rate | Usually temporary slowing during the procedure | Heart-rate checks; pausing or stopping the infusion |
| Pregnancy loss | A small risk of miscarriage or preterm loss related to the procedure | Doing it only when the answer will change care; experienced operator |
| Rh sensitisation | In Rh-negative mothers, the immune system may react to the baby’s blood | Anti-D injection after the procedure |
In labour, transcervical amnioinfusion has its own risks, including over-distension of the womb, raised pressure in the womb, cord prolapse and, very rarely, amniotic fluid embolism. These are managed by the labour-room team.
The most important safety principle is not technical at all: amnioinfusion should be done only when its result, or its effect, is likely to change what happens next. A good specialist will tell you plainly if they do not think it is worthwhile.
After the procedure
After the procedure you will usually rest for a while, and the baby’s heartbeat will be checked again before you leave. If you are Rh negative, the anti-D injection is given. Most women go home the same day unless the underlying condition requires admission — which is often the case with ruptured membranes, where the hospital team will continue care.
For the next day or two, take it easy, avoid heavy lifting and strenuous exercise, and avoid sexual intercourse until your doctor advises otherwise. Some mild cramping is common. Paracetamol is generally considered safe in pregnancy for discomfort; avoid other painkillers unless prescribed.
Seek prompt medical attention if you have:
- A gush or steady leak of fluid from the vagina
- Fever or shivering
- Regular or painful contractions
- Vaginal bleeding
- Severe or increasing abdominal pain
- Reduced or absent baby movements
- Offensive vaginal discharge
Results: what it can show and how long the fluid lasts
The “result” of a diagnostic amnioinfusion is mainly the detailed scan done once the fluid window is created. The specialist can often tell you immediately what was seen — for example, whether both kidneys and the bladder are visible, whether the heart and spine look normal, and whether fluid is leaking out. A written report follows, and your obstetrician will discuss what it means for the plan. If a genetic sample was taken, those results take longer and are discussed separately.
How long the infused fluid lasts depends entirely on the cause of the low fluid:
- Ruptured membranes: fluid often leaks out within hours to a few days. Seeing it leak can itself confirm the diagnosis.
- Absent or non-working kidneys: fluid is not replaced by the baby and gradually disappears.
- Placental insufficiency: fluid usually falls again, because the underlying reduction in the baby’s urine continues.
- No identifiable cause: fluid may last longer, and the follow-up plan will depend on repeated scans.
For this reason, a single amnioinfusion is rarely the end of the story. Follow-up scans of fluid, growth and Doppler blood flow, and a clear plan for monitoring and delivery, matter as much as the procedure itself.
Amnioinfusion vs amnioreduction vs amniocentesis
These three procedures sound alike and use similar needles under ultrasound, but they do very different things.
| Amnioinfusion | Amnioreduction | Amniocentesis | |
|---|---|---|---|
| What happens | Fluid is added to the sac | Excess fluid is removed | A small sample of fluid is taken |
| Used for | Very low fluid (oligohydramnios), unclear scans, suspected ruptured membranes; cord compression in labour | Severe excess fluid (polyhydramnios) causing symptoms or preterm labour risk | Genetic and chromosomal testing, infection testing |
| Typical volume | Often a few hundred millilitres infused | Often a litre or more drained slowly | Around 15 to 20 millilitres |
| Time with needle in place | About 20 to 45 minutes | About 30 to 60 minutes | A few minutes |
| Does it fix the cause? | No — fluid is often lost again | No — fluid often re-accumulates | Not a treatment; a test |
If you have been told you have too much fluid rather than too little, read our guide to amnioreduction for polyhydramnios. For the standard genetic test, see amniocentesis in Delhi.
Other ways low amniotic fluid is managed
Amnioinfusion is only one small part of how low fluid is managed, and for most women it is not needed at all. Depending on the cause and the stage of pregnancy, your obstetrician may recommend:
- Repeat scans to confirm the measurement, because fluid readings vary with the baby’s position
- Drinking enough water, which in studies modestly raises fluid measurements in women with isolated low fluid, although it does not treat underlying causes
- Growth scans and Doppler studies to check how well the placenta is supplying the baby — see our growth scan and Doppler page
- A detailed anomaly scan, especially to look at the kidneys and bladder — see the anomaly scan (TIFFA)
- Reviewing medicines that can reduce fluid
- Monitoring the baby’s wellbeing with heart-rate tracings and scans
- Treating ruptured membranes with the standard obstetric care of antibiotics, steroids where appropriate and infection monitoring
- Planning the timing and mode of delivery, which near term is often the most effective step of all
Be cautious of any promise that a particular food, supplement or “special injection” will reliably increase amniotic fluid. There is no medicine that safely and reliably does this, and anything you take in pregnancy should be agreed with your doctor.
Questions to ask your doctor
- What is the main purpose of the amnioinfusion in my case — diagnosis, confirming rupture, or treatment?
- What will we do differently depending on what it shows?
- What is the likely cause of my low fluid?
- Are the membranes intact or ruptured, and how does that change the risks?
- Will a genetic sample be taken at the same time, and is that necessary?
- Is this likely to need repeating?
- What are the alternatives, including waiting and monitoring?
- Do I need anti-D afterwards?
- Where will I be monitored afterwards, and who do I call if I have symptoms?
What to expect on the day
On the day, bring your referral letter, all previous scan reports, your blood group report and any recent blood tests. Wear comfortable two-piece clothing so the abdomen can be reached easily. You will be welcomed, your details and consent confirmed, and a scan done before anything else. The specialist will explain what they see before starting and will talk you through each step. Afterwards, you will rest and have a final check before going home or back to your obstetric team.
Prenatal procedures and the law
Prenatal diagnostic procedures in India are governed by the Pre-Conception and Pre-Natal Diagnostic Techniques (PCPNDT) Act. Any testing of amniotic fluid is done only to detect genetic, chromosomal, metabolic or structural conditions, at a registered centre. Determining or disclosing the sex of a fetus is a criminal offence. We do not determine it and do not disclose it under any circumstances.
Amnioinfusion in Delhi: where it is done
Edge Imaging & Diagnostics is a NABH-accredited diagnostic group in West Delhi, registered under the PCPNDT Act, offering ultrasound-guided transabdominal amnioinfusion together with the scans that matter when fluid is low — amniotic fluid assessment, anomaly scans, growth scans with fetal Doppler and fetal echocardiography — and related procedures such as amniocentesis, cordocentesis and amnioreduction. Procedures are performed by our consultant radiologists on an obstetrician’s referral. Amnioinfusion during labour is done in the labour room by your obstetric team and is not performed at our centre.
Before anything is booked, we review your referral and your recent scans. If a repeat scan or a detailed anomaly scan is the right next step rather than a procedure, we will tell you that plainly.
Send a photograph of your obstetrician’s referral and your latest scan report on WhatsApp and we will explain what is being asked for, the preparation, and today’s actual pricing.
💬 Send your referral on WhatsApp for guidance and today’s pricing | Call 9555999960
Related reading: Amnioreduction for polyhydramnios · Amniocentesis in Delhi · Cordocentesis (fetal blood sampling) · Anomaly scan (TIFFA) · Growth scan and Doppler · Fetal echocardiography · Pregnancy scan schedule
References
- Oligohydramnios — StatPearls, NCBI Bookshelf (US National Library of Medicine).
- Transabdominal amnioinfusion for improving fetal outcomes after oligohydramnios secondary to preterm prelabour rupture of membranes before 26 weeks — Cochrane Database of Systematic Reviews, 2013.
- Amnioinfusion for potential or suspected umbilical cord compression in labour — Cochrane Database of Systematic Reviews.
- Amnioinfusion Not Effective in Meconium Aspiration Syndrome — American Family Physician, 2006 (summary of the Fraser et al. multicentre randomised trial).
- Government of NCT of Delhi: PCPNDT — Delhi.
Frequently asked questions
What is amnioinfusion?
Amnioinfusion is a procedure in which warmed sterile fluid, usually normal saline or Ringer’s lactate, is placed into the amniotic sac around the baby. Before labour it is done through a fine needle in the abdomen under ultrasound guidance (transabdominal amnioinfusion); during labour it is done through a thin catheter in the cervix (transcervical amnioinfusion).
Why is amnioinfusion done?
Before labour, mainly to create a fluid window so the baby can be seen clearly on ultrasound when fluid is very low, to help confirm whether the waters have broken, and in selected cases of early severe low fluid. During labour, it is used to cushion the umbilical cord when the baby’s heart-rate pattern suggests cord compression.
What is the difference between transabdominal and transcervical amnioinfusion?
Transabdominal amnioinfusion is done before labour with a needle through the abdomen under continuous ultrasound, usually in a fetal medicine or imaging unit. Transcervical amnioinfusion is done during labour, after the waters have broken, through a soft catheter in the cervix, by the obstetric team in the labour room.
Does amnioinfusion increase amniotic fluid permanently?
Usually not. Amnioinfusion replaces fluid but does not fix the cause of low fluid. If the membranes are ruptured the fluid often leaks out within hours to days, and if the baby’s kidneys are not producing urine or the placenta is not working well, the fluid usually falls again.
Is amnioinfusion a treatment for oligohydramnios?
Amnioinfusion for oligohydramnios is mainly a diagnostic tool. It can allow a reliable scan and help find the cause of low fluid. As a treatment, especially after early rupture of the membranes, the evidence is limited and mixed, so it is offered only in selected cases after careful counselling.
How is the amnioinfusion procedure done?
After a scan to find a safe pocket of fluid, the skin is cleaned and numbed, a fine needle is guided into the amniotic sac under ultrasound, and warmed sterile fluid is infused slowly while the baby’s heart rate and the fluid level are checked. A detailed scan of the baby is then performed and the needle is removed.
Is amnioinfusion painful?
Most women find it uncomfortable rather than painful. There is a brief sting from the local anaesthetic, a pressing sensation as the needle enters the womb, and sometimes mild cramping or fullness during the infusion. General anaesthesia is not used.
How long does amnioinfusion take?
The needle part of a transabdominal amnioinfusion usually takes about 20 to 45 minutes. Including the preliminary scan, preparation and observation afterwards, the visit commonly takes one to two hours.
How much fluid is put in during amnioinfusion?
There is no fixed amount. Commonly a few hundred millilitres of warmed fluid are infused, enough to bring the deepest pocket back towards the normal range and give a good ultrasound view. Overfilling is avoided because it can trigger contractions.
What are the risks of amnioinfusion?
Amnioinfusion risks include leaking of fluid or rupture of the membranes, infection inside the womb, preterm contractions or labour, bleeding, temporary changes in the baby’s heart rate and, rarely, pregnancy loss. Risks are broadly similar to amniocentesis but can be higher because the procedure takes longer and the pregnancy is often already complicated.
Can amnioinfusion help after early rupture of membranes (PPROM)?
It has been studied, but a Cochrane review found the evidence too limited to recommend transabdominal amnioinfusion as routine treatment after PPROM before 26 weeks, and other trials have not shown clear benefit. Standard care with antibiotics, steroids where appropriate and infection monitoring remains the mainstay.
Is amnioinfusion used for meconium in labour?
Not routinely. A large international randomised trial of nearly two thousand women with thick meconium found that amnioinfusion did not reduce meconium aspiration syndrome or perinatal death. Amnioinfusion in labour may still be used for suspected cord compression.
How long does the fluid last after amnioinfusion?
It depends on the cause. With ruptured membranes, fluid often leaks out within hours to a few days. With absent or non-working kidneys, fluid gradually disappears. With placental insufficiency it usually falls again. Where no cause is found, it may last longer, and repeat scans guide the plan.
Can a genetic test be done at the same time as amnioinfusion?
Yes, if it has been discussed and agreed beforehand, a small sample of amniotic fluid can be taken through the same needle for genetic or chromosomal testing. Testing under the PCPNDT Act looks only for genetic, chromosomal, metabolic or structural conditions.
Can drinking water increase amniotic fluid?
Drinking enough water has been shown to modestly raise fluid measurements in women with isolated low fluid, but it does not treat underlying causes such as ruptured membranes or placental problems. No medicine reliably and safely increases amniotic fluid, so take nothing without your doctor’s advice.
Is amnioinfusion available in Delhi?
Yes. Transabdominal amnioinfusion is performed at fetal medicine and imaging centres in Delhi on an obstetrician’s referral. Edge Imaging & Diagnostics in West Delhi performs ultrasound-guided transabdominal amnioinfusion along with anomaly scans, growth scans with Doppler and fetal echocardiography. Send your referral on WhatsApp to 9555999960.
What symptoms after amnioinfusion need urgent attention?
Seek prompt medical attention for a gush or steady leak of fluid, fever or shivering, regular or painful contractions, vaginal bleeding, severe or increasing abdominal pain, reduced baby movements or offensive vaginal discharge.
The bottom line
Amnioinfusion puts warmed sterile fluid back around the baby. Before labour, done through the abdomen under ultrasound, its greatest value is diagnostic: it lets the baby be seen clearly when fluid is very low and helps find out why. During labour, it can cushion a squeezed umbilical cord.
It does not repair torn membranes, non-working kidneys or a struggling placenta, so the fluid is often lost again. Used for the right reason, by an experienced team, and followed by careful monitoring, it can give you and your doctor clearer answers.
Written by the clinical content team at Edge Imaging & Diagnostics, West Delhi — a NABH-accredited diagnostic centre registered under the PCPNDT Act. Medically reviewed by Dr. Nishant Thapar, Consultant Radiologist. Last reviewed: October 2026.
Medical disclaimer: this article is general information about low amniotic fluid and amnioinfusion. It is not medical advice, a diagnosis, or guidance on any decision about a pregnancy.
Fluid measurement cut-offs, volumes, timings and risk descriptions quoted here are approximate and vary between guidelines, centres and individual pregnancies. Your own obstetrician and the specialist performing the procedure should give you information specific to your situation.
Leaking fluid, bleeding, fever, contractions, severe pain or reduced fetal movements need prompt in-person assessment.
Prenatal diagnostic testing in India is governed by the PCPNDT Act. Determining or disclosing the sex of a fetus is a criminal offence, and this centre does not do so under any circumstances.