
 PV
 TG
 MN
 EM
 EI
 ND

 CT Scan
 PET CT
 Digital X-ray
 Ultrasound
 Amniocentesis

 Fetal Reduction
 Thermalytix Breast Screening
 Cardiology
 Lab Tests
 GAMCA Pre-Medical
Triplet to twin reduction is a procedure in which one of three babies in a triplet pregnancy is reduced, so that the pregnancy continues as twins. It is done to lower the very high risk of extremely premature birth that comes with triplets. It is usually performed at about 11 to 14 weeks, by an ultrasound-guided injection into a baby that has its own placenta.
Hearing “there are three heartbeats” — often after years of fertility treatment — can bring joy and fear at the same moment. Soon after, your doctor may explain that triplets carry serious risks, and that reducing triplets to twins is one option to consider. For many couples it is one of the hardest conversations of their lives.
This guide explains triplet to twin reduction honestly and in simple language: why triplets are high-risk, who the procedure is for, how it is done, what the research shows about miscarriage and preterm birth, how the placentas change the options, what happens afterwards, and the law in India. It is general information, not a recommendation. The decision always belongs to you, with your obstetrician and fetal medicine specialist.
People search for this as “triplet to twin reduction”, “reducing triplets to twins”, “triplet reduction”, “triplet pregnancy reduction”, “fetal reduction triplets to twins” or, in Hinglish, “triplets se twins reduction”. All of these are answered here, with a short Hinglish section near the end.
Triplet to twin reduction at a glance
- What it is: reducing a triplet pregnancy to twins by stopping the development of one baby
- Why: to lower the high risk of very premature birth and its effects on the babies, and the extra risks to the mother
- When: usually at about 11 to 14 weeks, after a detailed scan of all three babies
- How: an ultrasound-guided injection into a baby with its own placenta; specialised methods if two babies share a placenta
- What studies show: in triplets with three placentas, reducing to twins cut preterm birth before 34 weeks from about half to about one in six
- Main risk: miscarriage of the whole pregnancy — similar to or somewhat higher than continuing with triplets, depending on the study
- Afterwards: the pregnancy is cared for as a twin pregnancy
- The law: governed by the MTP Act; the sex of a fetus is never determined, disclosed or used in any decision
What this guide covers
- What triplet to twin reduction means
- Why triplet pregnancies happen
- The risks of carrying triplets
- Who triplet to twin reduction is for
- Chorionicity: why the placentas matter in triplets
- The options: keep all three, reduce to twins, or reduce to one
- Triplet to twin reduction: what the evidence shows
- Triplets to twins or to one baby?
- Dichorionic triplets: when two babies share a placenta
- Best time for triplet to twin reduction: 11 to 14 weeks
- How the baby to be reduced is chosen
- Before the procedure
- How triplet to twin reduction is done, step by step
- Does triplet reduction hurt?
- Risks of the procedure
- After triplet to twin reduction
- Caring for your twin pregnancy after reduction
- A week-by-week timeline
- IVF triplets: questions couples in India ask
- The emotional side
- Preventing triplet pregnancies in future
- Myths and facts
- Triplet reduction and the law in India: MTP and PCPNDT Acts
- Questions to ask before deciding
- Seedhi baat: triplets se twins reduction
- Triplet to twin reduction in Delhi: how we can help
- References
- Frequently asked questions
What triplet to twin reduction means
Triplet to twin reduction — part of the wider procedure known as fetal reduction or multifetal pregnancy reduction — means ending the development of one of the three fetuses in a triplet pregnancy, so that the pregnancy continues as twins. It is what most doctors mean when they talk about reducing triplets to twins or simply “triplet reduction”.
The babies who continue are not removed or disturbed. The reduced fetus is gradually absorbed by the body over the following weeks, and the pregnancy continues with fewer babies. Fetal reduction was developed specifically for high-order multiple pregnancies, where the risks are greatest, and this remains its most widely accepted use.
If you are carrying twins rather than triplets, our separate guide to twin to singleton reduction covers that situation.
Why triplet pregnancies happen
Naturally conceived triplets are rare. Most triplet pregnancies today follow fertility treatment — either the transfer of more than one embryo in IVF, or ovulation-stimulating medicines and injections that release several eggs at once. Occasionally, one embryo splits to form identical twins alongside other babies, producing triplets with a shared placenta.
Understanding how the pregnancy happened is not about blame. Many couples have waited years for a pregnancy and feel conflicting emotions on hearing there are three babies. It does, however, explain why fertility specialists now try to avoid triplet pregnancies wherever possible, which we discuss later.
The risks of carrying triplets
The womb can carry three babies, but the more babies there are, the earlier labour tends to start. Prematurity is the main driver of the risks to the babies, and it rises steeply with each additional baby.
| Area | Why it matters in a triplet pregnancy |
|---|---|
| Preterm birth | About half of triplets with three placentas, managed without reduction, are born before 34 weeks in pooled studies |
| Very early birth | Births before 28 to 32 weeks bring risks of breathing problems, bleeding in the brain, infection, cerebral palsy and long stays in neonatal intensive care |
| Growth | Babies are smaller, and one or more may grow poorly |
| Miscarriage and loss | The chance of losing one or more babies, or the whole pregnancy, is higher than with twins |
| Maternal health | Higher rates of pre-eclampsia, gestational diabetes, anaemia, breathlessness, heavy bleeding after birth, and almost always a caesarean birth |
| Family impact | Long hospital stays, the financial and emotional cost of caring for several premature babies at once |
None of this means that every triplet pregnancy goes badly — many families have healthy triplets. But the risks are real and substantial, and they are the reason fetal reduction is discussed at all.
Who triplet to twin reduction is for
Triplet to twin reduction is considered when a triplet pregnancy has been confirmed on an early scan and the parents, after counselling, want to lower the risk of a very early birth. It is most straightforward in trichorionic triplets, where each baby has its own placenta — the usual pattern after IVF or ovulation treatment.
It may also be discussed when there are extra reasons for concern, for example:
- A mother with a medical condition, such as high blood pressure, diabetes or a heart or kidney problem, that makes carrying three babies riskier
- A previous very early birth or a weak cervix
- A uterus with an unusual shape or past surgery
- One baby with a raised nuchal translucency or another concern on the early scan
Many couples also simply feel that two babies give them the best chance of a healthy outcome. Others choose to continue with all three. Both choices are valid, and a good team respects either.
Chorionicity: why the placentas matter in triplets
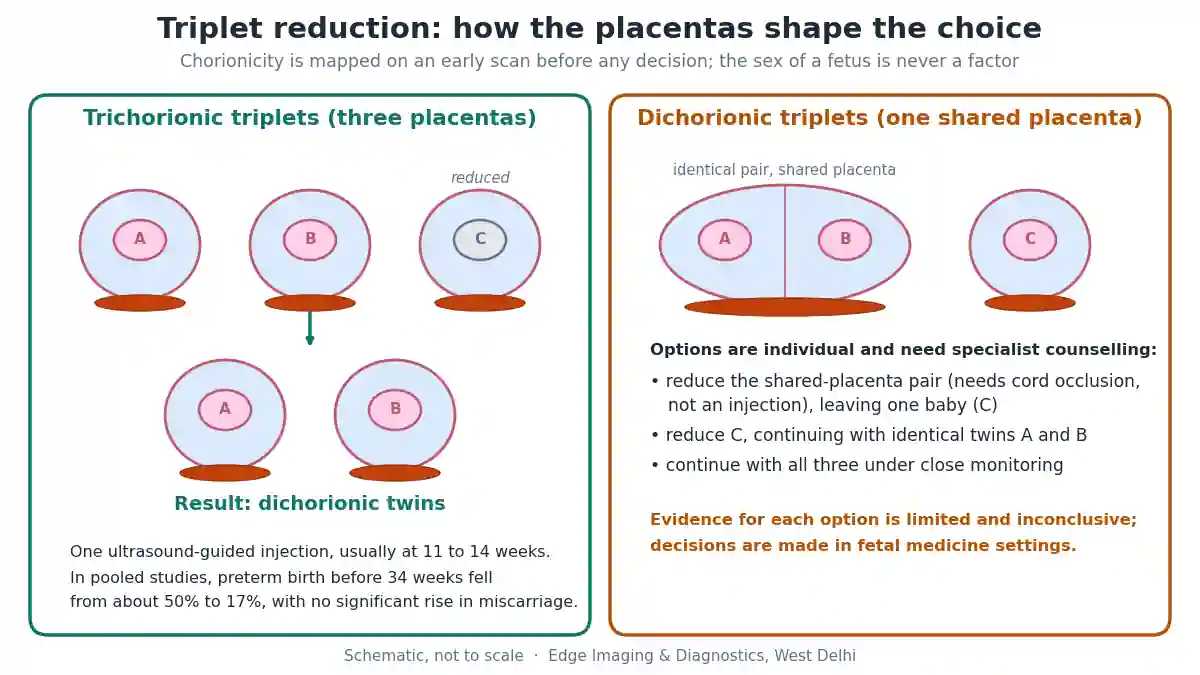
Chorionicity describes how many placentas the babies have. It is the most important scan finding in any discussion of reduction, and it is best determined on an early ultrasound, ideally before 14 weeks.
- Trichorionic triplets each have their own placenta and their own blood circulation. This is the most common arrangement after fertility treatment, and reduction by injection is straightforward in principle.
- Dichorionic triplets include a pair of identical twins who share one placenta, plus a third baby with its own placenta. The shared placenta connects the pair’s circulations.
- Monochorionic triplets, where all three share one placenta, are rare and need highly specialised care.
The shared circulation matters because anything injected into one baby of a monochorionic pair would reach the other, and the death of one can cause sudden harm to its partner through the connecting vessels. So an injection is used only for a baby with its own placenta. Reducing a baby that shares a placenta requires specialised cord-occlusion techniques performed in fetal therapy centres.
The options: keep all three, reduce to twins, or reduce to one
For most triplet pregnancies, there are three broad options, and good counselling covers all of them. Reducing to twins is the most common choice, but it is only one of the three.
| Option | What it means | Main considerations |
|---|---|---|
| Keep all three babies (expectant management) | Close monitoring of the triplet pregnancy | Avoids the procedure risk; keeps the high risk of very early birth |
| Reduce to twins | One of the three babies is reduced | The most common choice; large reduction in very early birth |
| Reduce to one baby | Triplets to a singleton | Lowers prematurity further; less evidence; considered individually |
In dichorionic triplets, the options are more complicated, as shown in the diagram above: reducing the identical pair needs a cord-occlusion method and leaves one baby, while reducing the separate baby leaves identical twins who still carry the risks of a shared placenta. The evidence for these choices is limited, and they are decided in fetal medicine settings after detailed counselling.
Triplet to twin reduction: what the evidence shows
There are no randomised trials, because families understandably choose their own path. But several large observational studies and reviews point in a consistent direction for trichorionic triplets.
- A 2017 systematic review and meta-analysis in Human Reproduction pooled studies of trichorionic triplets. Preterm birth before 34 weeks was 50.2% when all three babies were continued and 17.3% after reducing triplets to twins. Miscarriage before 24 weeks was 7.4% with expectant management and 8.1% after reduction — a difference that was not statistically significant.
- An earlier study and review from 2006 found that reduction to twins lowered early preterm birth before 32 weeks from 26.7% to 10.4%, but raised miscarriage from 4.4% to 8.1%. The authors estimated that about seven reductions prevent one early preterm birth, while about twenty-six reductions cause one additional miscarriage.
- A large Chinese single-centre study from 2022 found that triplets reduced to twins had a pregnancy loss rate of 6.6%, almost identical to the 6.5% in pregnancies that were twins from the start, and the same median age at delivery of about 37 weeks.
| Trichorionic triplets (pooled studies, 2017) | Continued as triplets | Reduced to twins |
|---|---|---|
| Miscarriage before 24 weeks | 7.4% | 8.1% (difference not significant) |
| Born before 34 weeks | 50.2% | 17.3% |
What this means in plain terms: reducing triplets to twins substantially lowers the chance of a very premature birth. The effect on miscarriage is uncertain — some studies show little or no increase, others a modest increase. Families weigh these two sides differently, and there is no single right answer.
For dichorionic triplets, the same review found the evidence inconclusive, because the studies were small.
Triplets to twins or to one baby?
Some families ask whether to reduce triplets to twins or to one baby. Reducing to one baby lowers the risk of preterm birth further than reducing to twins, but it means two procedures within the same pregnancy (often at one sitting), and the evidence comparing it directly with reduction to twins is more limited. It may be considered in particular situations — for example a maternal medical condition, a history of very early birth, a uterine abnormality, or dichorionic triplets — and is decided individually after specialist counselling.
Dichorionic triplets: when two babies share a placenta
In dichorionic triplets, two of the babies are identical twins sharing one placenta, and the third has its own. This changes the choices:
- Reducing the separate baby (the one with its own placenta) is technically possible by injection, but it leaves identical twins who still carry the extra risks of a shared placenta.
- Reducing one of the identical pair cannot be done by a simple injection, because the shared circulation would affect the other baby. It needs a specialised cord-occlusion technique, available only in fetal therapy centres.
- Reducing the identical pair leaves a single baby and also needs specialised techniques.
The 2017 review found the evidence for dichorionic triplets inconclusive, because the studies were small. These pregnancies need careful, individual counselling with a fetal medicine specialist.
Best time for triplet to twin reduction: 11 to 14 weeks
Triplet to twin reduction is usually performed at about 11 to 14 weeks. By then:
- Each baby can be assessed in detail, including the nuchal translucency measurement and an early anatomy check
- Chorionicity can be confirmed reliably
- Some pregnancies will have already reduced naturally, as one baby sometimes stops developing in the first weeks
- Chorionic villus sampling can be performed first, if chosen
In dichorionic twin pregnancies, a large national study found the best outcomes when reduction was done before 14 weeks, and the same principle is generally applied to triplets. Some centres reduce earlier, at 7 to 10 weeks; the choice is made by the specialist and explained beforehand.
How the baby to be reduced is chosen
The choice is made on medical and technical grounds only:
- Screening findings: any baby with a raised nuchal translucency, a structural concern, or an abnormal genetic result
- Chorionicity: keeping the two babies whose placentas give the safest remaining twin pregnancy
- Accessibility: the baby that can be reached most safely with the needle
- Position: the sac lying over the cervix is generally left undisturbed, to reduce the risk of infection and leakage
The sex of the babies plays no part whatsoever. It is not determined, not disclosed and not considered. Choosing on the basis of sex is a criminal offence in India under the PCPNDT Act.
Before the procedure
- A detailed first-trimester scan of every baby: number, chorionicity, heartbeats, size, nuchal translucency and early anatomy.
- Genetic options. Some families choose chorionic villus sampling (CVS) on the babies likely to remain, so that if one has a chromosomal condition, the plan can change. This adds time and a small risk, and is discussed individually.
- Blood tests, including blood group; Rh-negative mothers receive anti-D after the procedure.
- Counselling on all the options — including continuing with all the babies — the risks, and the legal requirements. You should never feel rushed, and you can change your mind at any point before the procedure.
- Written consent, as required by law.
How triplet to twin reduction is done, step by step
When the baby to be reduced has its own placenta, the procedure is performed through the abdomen under continuous ultrasound guidance.
- Final scan. All babies, their positions, heartbeats and placentas are checked again, and the babies to be reduced are confirmed.
- Preparation. The abdomen is cleaned with antiseptic and draped, and local anaesthetic is injected into the skin.
- Needle guidance. A fine needle is passed through the abdominal wall and the wall of the womb into the chest area of the selected fetus, watched on the screen the whole time.
- Injection. A small amount of potassium chloride is injected, which stops that fetus’s heart.
- Confirmation. The heartbeat is watched for several minutes to confirm it has stopped, and the remaining babies’ heartbeats are checked.
- If reducing to one baby. When a family has chosen to reduce triplets to one baby, the steps are repeated for a second fetus, usually at the same sitting.
- Completion. The needle is removed and a small dressing applied.
The procedure usually takes around 20 to 40 minutes. Some centres use a transvaginal approach in very early pregnancy. Where a baby that shares a placenta must be reduced, a cord-occlusion technique is used instead, in a specialised fetal therapy centre.
Does triplet reduction hurt?
Most women describe it as uncomfortable rather than painful: a brief sting from the local anaesthetic, a pressing sensation as the needle enters the womb, and sometimes cramping afterwards. General anaesthesia is not used. Many women say the emotional weight of the day is harder than the physical sensation, so it helps to bring someone you trust.
Risks of the procedure
| Risk | What it means | How it is reduced |
|---|---|---|
| Miscarriage of the whole pregnancy | Loss of the remaining babies; in studies broadly similar to or somewhat above the background risk of triplets | Appropriate timing, experienced operator, careful technique |
| Infection | Infection inside the womb | Strict sterile technique; avoiding the sac over the cervix |
| Leaking fluid or bleeding | Usually minor | Fine needle, continuous ultrasound guidance |
| Preterm birth of the remaining twins | Still higher than in a pregnancy that was always twins | Close antenatal monitoring |
| Rh sensitisation | In Rh-negative mothers | Anti-D injection |
| Emotional distress | Grief, guilt or sadness, sometimes long-lasting | Counselling before and after; family support |
Ask your specialist for the figures from their own centre and for your own situation; published numbers vary with timing, technique and the type of pregnancy.
After triplet to twin reduction
You will rest and be observed, and the heartbeats of the remaining babies are checked before you go home, usually the same day. Rest for a day or two, avoid heavy lifting, strenuous exercise and intercourse until advised, and keep the follow-up scan, usually within one to two weeks. Seek prompt attention for fever, heavy bleeding, leaking fluid, severe pain or offensive discharge.
The pregnancy then continues as a twin pregnancy, with the scans that type of pregnancy needs — including the anomaly scan (TIFFA), regular growth scans and, for twins, closer monitoring. The reduced fetus is gradually absorbed and may be visible as a small remnant on later scans and at delivery; this is expected. Make sure anyone interpreting later blood screening tests knows the pregnancy was originally triplets, as some markers can be affected.
Caring for your twin pregnancy after reduction
After the reduction, the pregnancy is cared for as a twin pregnancy — with the closer monitoring that twins need. In practice this usually means:
- Regular growth scans, often every few weeks from mid-pregnancy, to check that both babies are growing evenly
- Doppler studies of blood flow when growth is slow or uneven
- A detailed anomaly scan at around 18 to 22 weeks
- Assessment of the cervix where there is a higher risk of early labour
- Regular checks of blood pressure and urine for pre-eclampsia, and screening for gestational diabetes
- A planned discussion of the timing and mode of delivery in the third trimester
Studies show that twins remaining after reduction from triplets do broadly as well as twins conceived as twins, so the usual twin care pathway applies. Your obstetrician will tailor the schedule to your pregnancy.
A week-by-week timeline
Every pregnancy is different, but a typical path looks like this:
- 6 to 8 weeks: early scan confirms three babies and their heartbeats.
- 8 to 10 weeks: follow-up scan; chorionicity is checked; counselling begins. Some pregnancies reduce naturally at this stage.
- 11 to 14 weeks: detailed scan of each baby, including nuchal translucency; CVS if chosen; reduction if decided.
- 1 to 2 weeks after reduction: follow-up scan to check the twins.
- Around 18 to 22 weeks: detailed anomaly scan of both babies.
- From mid-pregnancy: regular growth scans and twin pregnancy care, as your obstetrician advises.
For more on which scans are done when, see our pregnancy scan schedule.
IVF triplets: questions couples in India ask
Most triplet pregnancies in India today follow IVF or ovulation treatment, and couples often have very practical questions:
- “Will reduction harm the other two babies?” The procedure is designed to leave the remaining twins undisturbed; the main risk is miscarriage of the whole pregnancy, discussed above.
- “Can we wait and see?” Yes, for a short time — some triplets reduce naturally in the first weeks. But reduction is safest done by about 14 weeks, so the decision should not be left too late.
- “Will our IVF doctor do it?” Sometimes. Often, the IVF doctor or obstetrician refers you to a centre experienced in ultrasound-guided procedures.
- “Will people know?” Your medical information is confidential. What you share with family is your decision.
- “Will the twins be normal twins after this?” Studies suggest twins after reduction from triplets do broadly as well as twins conceived as twins.
The emotional side
Many parents feel relief, sadness, guilt and grief together — especially after a long journey through fertility treatment. These feelings are normal and do not mean the decision was wrong. Take the time you need, involve your partner, consider speaking to a counsellor, and decide for yourselves what to share with family. A respectful team supports whatever decision you make, without judgement.
Preventing triplet pregnancies in future
The best way to avoid facing this decision again is to prevent triplet pregnancies in the first place. Fertility specialists increasingly recommend transferring fewer embryos in IVF — often a single embryo in suitable cases — and careful scan monitoring during ovulation-stimulating treatment, so that a cycle can be adjusted or cancelled if too many eggs are developing. If you are planning fertility treatment, it is worth asking your specialist how they minimise the chance of triplets.
Myths and facts
- Myth: “Triplet to twin reduction always causes miscarriage.” Fact: most pregnancies continue; studies report miscarriage rates broadly similar to, or somewhat above, continuing with triplets.
- Myth: “The doctor chooses which baby by sex.” Fact: sex is never determined, disclosed or considered; it is a criminal offence in India.
- Myth: “Reduction can be done any time.” Fact: it is usually done at about 11 to 14 weeks, and later reduction may carry more risk.
- Myth: “It is a major operation.” Fact: it is an ultrasound-guided needle procedure under local anaesthetic, and most women go home the same day.
- Myth: “Any injection works for any triplets.” Fact: a baby who shares a placenta needs specialised methods.
Triplet reduction and the law in India: MTP and PCPNDT Acts
In India, fetal reduction is carried out within the framework of the Medical Termination of Pregnancy (MTP) Act and its rules, as amended in 2021. It must be performed by qualified registered medical practitioners, with the woman’s written informed consent and the documentation the law requires. Your doctor will explain the requirements that apply to your situation.
Prenatal scanning and diagnosis are governed by the Pre-Conception and Pre-Natal Diagnostic Techniques (PCPNDT) Act. Determining or disclosing the sex of a fetus is a criminal offence, and sex is never used in any decision about which babies are reduced. We do not determine it and do not disclose it under any circumstances.
Questions to ask before deciding
- How many placentas do my babies have, and how certain is that?
- What are the risks if we continue with all the babies?
- What would reducing to twins, or to one baby, change in my case?
- What is the risk of losing the whole pregnancy, at this centre and at this stage?
- Should CVS be done before the reduction?
- How will the babies to be reduced be chosen?
- Who will perform the procedure, and how experienced are they?
- What follow-up and emotional support is available?
- What documentation and consent does the law require?
Seedhi baat: triplets se twins reduction
Triplets (teen bachche) wali pregnancy me bachche bahut jaldi, yaani time se kaafi pehle paida hone ka khatra zyada hota hai. Triplet to twin reduction me teen me se ek bachche ko ultrasound dekhte hue injection se reduce kiya jaata hai, taaki pregnancy twins ki tarah aage chale.
Yeh aam taur par 11 se 14 hafte ke beech hota hai. Pehle har bachche ka detailed scan aur placenta (chorionicity) check hota hai. Research ke hisaab se teen placenta wale triplets me 34 hafte se pehle delivery ka chance lagbhag aadha hota hai, jo twins me reduce karne ke baad lagbhag 6 me se 1 reh jaata hai. Poori pregnancy girne ka risk bina reduction ke barabar ya thoda zyada ho sakta hai.
Bachche ka gender kabhi nahi dekha ya bataya jaata — yeh kanoon ke khilaaf hai. Faisla hamesha aapka hai, apne doctor ke saath, bina kisi dabav ke.
Triplet to twin reduction in Delhi: how we can help
Edge Imaging & Diagnostics is a NABH-accredited diagnostic centre in West Delhi, registered under the PCPNDT Act. For triplet pregnancies we provide early dating and chorionicity scans, nuchal translucency assessment of each baby, CVS and amniocentesis, anomaly scans, fetal echocardiography and growth scans with Doppler. Ultrasound-guided fetal reduction for a baby with its own placenta is performed on an obstetrician’s referral, after counselling and with full legal documentation. Where the baby to be reduced shares a placenta and a cord-occlusion procedure is needed, we will explain this and guide you on referral to a specialised fetal therapy centre.
If reduction is not the right step for you, we will say so plainly, and we support families who choose to continue with all three babies.
Send a photograph of your obstetrician’s referral and your latest scan report on WhatsApp for a confidential discussion of the next step, the preparation, and today’s actual pricing.
💬 Send your referral on WhatsApp for confidential guidance | Call 9555999960
Related reading: Fetal reduction in Delhi: complete guide · Twin to singleton reduction · CVS test · Anomaly scan (TIFFA) · Pregnancy scan schedule
References
- Risks of miscarriage or preterm delivery in trichorionic and dichorionic triplet pregnancies with embryo reduction versus expectant management: a systematic review and meta-analysis — Anthoulakis C, et al. Human Reproduction, 2017.
- Risks of miscarriage and early preterm birth in trichorionic triplet pregnancies with embryo reduction versus expectant management: new data and systematic review — Papageorghiou AT, et al. Human Reproduction, 2006.
- Fetal Reduction Could Improve but Not Completely Reverse the Pregnancy Outcomes of Multiple Pregnancies: Experience From a Single Center — Zhu Y, et al. Frontiers in Endocrinology, 2022.
- Government of NCT of Delhi: PCPNDT — Delhi.
Frequently asked questions
What is triplet to twin reduction?
Triplet to twin reduction is a procedure that reduces a triplet pregnancy to twins, to lower the high risk of very premature birth. It is usually done at about 11 to 14 weeks by an ultrasound-guided injection into a fetus that has its own placenta.
Why is reducing triplets to twins recommended?
Because triplet pregnancies carry a high risk of very early birth and its complications. In pooled studies of triplets with three placentas, preterm birth before 34 weeks fell from about 50% when all three continued to about 17% after reducing triplets to twins.
Does triplet reduction increase the risk of miscarriage?
The evidence is mixed. A 2017 meta-analysis found miscarriage of 8.1% after reduction versus 7.4% when triplets continued, a non-significant difference, while a 2006 study found 8.1% versus 4.4%. Your specialist can explain the figures for your situation.
What is the success rate of triplet to twin reduction?
In pooled studies of triplets with three placentas, about 92% of pregnancies did not miscarry before 24 weeks after reduction to twins, and preterm birth before 34 weeks fell from about 50% to about 17%. Your specialist can give figures for your situation.
Can triplets be reduced to one baby?
Yes, in some situations, such as a maternal medical condition, a history of very early birth or dichorionic triplets. It lowers prematurity further than reducing to twins, but it requires two reductions and the evidence is more limited, so it is decided individually.
What is chorionicity and why does it matter in triplets?
Chorionicity is the number of placentas. In trichorionic triplets each baby has its own placenta and reduction by injection is possible. In dichorionic triplets two identical babies share a placenta, so an injection cannot be used for either of them and specialised methods are needed.
When is triplet reduction done?
Usually at about 11 to 14 weeks, after a detailed scan of each baby, including nuchal translucency and chorionicity. Some centres reduce earlier, at 7 to 10 weeks. The specialist explains the timing they recommend.
How is triplet pregnancy reduction done?
Under continuous ultrasound guidance and local anaesthetic, a fine needle is passed through the abdomen into the chest area of the selected fetus and a small amount of potassium chloride is injected to stop its heart. The remaining babies’ heartbeats are then checked.
How are the babies to be reduced chosen?
On medical and technical grounds only: abnormal screening or test results, chorionicity, which babies can be reached safely, and avoiding the sac over the cervix. The sex of the babies is never determined, disclosed or considered, as required by the PCPNDT Act.
Is triplet reduction painful?
Most women find it uncomfortable rather than painful, with a brief sting from the local anaesthetic, pressure as the needle enters the womb, and sometimes cramping afterwards. General anaesthesia is not used.
What happens to the reduced fetuses?
They are gradually absorbed by the body over the following weeks and may be seen as small remnants on later scans or at delivery. This is expected and does not harm the remaining babies.
Do twins after triplet reduction do as well as natural twins?
Broadly similar in some studies: a 2022 study found a pregnancy loss rate of 6.6% after triplets were reduced to twins versus 6.5% in original twins, with the same median delivery at about 37 weeks. Results vary between studies and centres.
Triplet reduction ke baad kitna aaram chahiye?
Zyaadatar mahilayein usi din ghar chali jaati hain aur ek-do din aaram karti hain. Bhaari kaam, zyada exercise aur intercourse doctor ki salah tak avoid karein. Follow-up scan aam taur par 1 se 2 hafte me hota hai.
Is fetal reduction of triplets legal in India?
Fetal reduction in India is carried out within the framework of the Medical Termination of Pregnancy Act and its rules, by qualified registered medical practitioners, with written informed consent and the required documentation. Any selection based on the sex of a fetus is a criminal offence under the PCPNDT Act.
Should CVS be done before triplet to twin reduction?
Some families choose chorionic villus sampling on the babies likely to remain, so the plan can change if one has a chromosomal condition. It adds time and a small risk and is discussed individually with your specialist.
Triplets se twins reduction kab karwana chahiye?
Aam taur par 11 se 14 hafte ke beech, har bachche ke detailed scan aur placenta check ke baad. Sahi samay aapke doctor aapki report dekh kar batayenge.
Where is triplet to twin reduction done in Delhi?
Edge Imaging & Diagnostics in West Delhi provides chorionicity scans, CVS, amniocentesis and ultrasound-guided fetal reduction for a baby with its own placenta on an obstetrician’s referral, and guides referral where a placenta is shared. Send your referral on WhatsApp to 9555999960 for confidential guidance and today’s actual pricing.
The bottom line
Triplet pregnancies carry a high risk of very premature birth. Triplet to twin reduction substantially lowers that risk; the effect on miscarriage is uncertain and may be a small increase. The number of placentas decides which options are possible, and the best time is usually 11 to 14 weeks.
There is no single right answer. Take the time you need, ask every question, and make the decision that is right for your family, with an experienced team that supports you whatever you choose.
Written by the clinical content team at Edge Imaging & Diagnostics, West Delhi — a NABH-accredited diagnostic centre registered under the PCPNDT Act. Medically reviewed by Dr. Nishant Thapar, Consultant Radiologist. Last reviewed: October 2026.
Medical disclaimer: this article is general information about triplet to twin reduction. It is not medical advice, a recommendation, or guidance on any decision about a pregnancy.
Risk and outcome figures quoted here come from published observational studies and vary between centres, techniques, timing and individual pregnancies. Your own obstetrician and the specialist performing the procedure should give you figures specific to your situation.
Fetal reduction in India is performed within the framework of the MTP Act. Prenatal diagnosis is governed by the PCPNDT Act. Determining or disclosing the sex of a fetus is a criminal offence, and this centre does not do so under any circumstances.